
-
Miami, Florida
-
Mon-Fri 8 am- 6pm (EST)
Patients from all over the US come to see Dr. Trapana due to his world class expertise in Spine
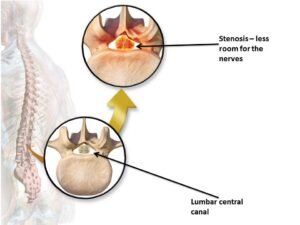
Lumbar Spinal Stenosis (LSS) is the leading indication for spine surgery in adults over the age of 65. As the lumbar spine undergoes decades of mechanical wear, disc height loss triggers a cascade of compensatory changes: facet joints hypertrophy (enlarge), osteophytes (bone spurs) form along vertebral margins, and the ligamentum flavum thickens and buckles into the spinal canal. The resulting mechanical narrowing chokes the neural elements within the central canal, lateral recesses, and neural foramina.
Clinically, this manifests as neurogenic claudication—a hallmark syndrome of progressive heaviness, burning, cramping, and numbness in the buttocks, thighs, and calves that worsens with standing and walking, but resolves when leaning forward or sitting. Patients often adopt a hunched posture or lean over grocery carts (“shopping cart sign”) to open up the narrowed canal.
Historically, the surgical remedy for multi-level stenosis was a wide, unconstrained open laminectomy, frequently paired with multi-level pedicle screw instrumentation and fusion. While this cleared the canal, wide bone and facet resection often created iatrogenic spinal instability, while rigid fusion sacrificed lumbar motion, accelerated adjacent-level breakdown, and imposed prolonged recoveries.
In South Florida, Dr. Evan Trapana is a fellowship-trained orthopedic spine surgeon and Assistant Professor of Orthopaedic Spine Surgery at the University of Miami Miller School of Medicine and UHealth Tower. Having completed his orthopedic surgery residency at the University of Miami/Jackson Memorial Hospital and advanced spine surgery fellowship training at the University of California San Diego (UCSD) Medical Center, Dr. Trapana specializes in minimally invasive spine surgery (MISS) and motion-preserving spine reconstruction. By employing targeted microscopic bilateral decompression via unilateral laminotomy (“over-the-top” decompression) alongside motion-preserving interlaminar stabilization, Dr. Trapana relieves claudication symptoms while maintaining the spine’s natural kinematics.
Lumbar central stenosis and lateral recess stenosis develop through three overlapping degenerative processes:
[DEGENERATIVE DISC COLLAPSE]
(Loss of hydration & disc height, circumferential annular bulging)
│
▼
[FACET JOINT OVERLOAD & HYPERTROPHY]
(Facet arthrosis, capsular thickening, osteophyte projection into lateral recess)
│
▼
[LIGAMENTUM FLAVUM HYPERTROPHY & BUCKLING]
(Loss of elastin, increased collagen deposition, forward redundant folding)
│
▼
[CIRCUMFERENTIAL SPINAL CANAL CONSTRICTION]
(Thecal sac cross-sectional area reduced from normal >100 mm² to critical <75–50 mm²)
Because lumbar stenosis predominantly affects older adults who often have coexisting peripheral artery disease (PAD), distinguishing between neurogenic claudication and vascular claudication is critical:
| Diagnostic Metric | Neurogenic Claudication (Spine) | Vascular Claudication (Circulatory) |
| Primary Etiology | Mechanical compression & ischemia of cauda equina | Arterial insufficiency / peripheral vascular disease |
| Pain Characteristics | Dull ache, cramping, numbness, “heavy legs” | Sharp, cramping muscle pain in calves |
| Aggravating Factors | Prolonged standing and walking upright | Walking a predictable, fixed distance |
| Relieving Factors | Sitting down, bending forward, crouching | Stopping and standing still (neutral posture) |
| Bicycle / Treadmill Test | Pain-free on inclined treadmill or stationary bike | Pain recurs rapidly regardless of posture |
| Physical Exam Findings | Normal pedal pulses; neurological reflexes altered | Diminished/absent pedal pulses; skin pallor/coldness |
Traditional open laminectomy required excising the central spinous processes, interspinous/supraspinous ligaments, and entire bilateral laminae, devascularizing the paraspinal musculature and destabilizing the posterior tension band.
Dr. Trapana utilizes a minimally invasive unilateral laminotomy for bilateral decompression (ULBD), also known as the “over-the-top” technique:
[Micro-Incision & Muscle-Splitting Tubular Dilation on Symptomatic Side]
│
▼
[Ipsilateral Hemi-Laminotomy & Ligamentum Flavum Resection]
(Direct microscopic decompression of the ipsilateral traversal root)
│
▼
[Angling the Tubular Retractor & Operating Microscope Sub-Spinously]
(Drill crosses midline beneath the base of the spinous process)
│
▼
[Contralateral “Over-the-Top” Sub-Laminar Undercutting]
(Excises contralateral ligamentum flavum & decompresses opposite lateral recess)
│
▼
[360° Thecal Sac Expansion Preserving Supraspinous Ligament & Contralateral Muscle]
Through this single-sided keyhole corridor, both sides of the spinal canal are thoroughly decompressed while leaving the posterior stabilizing column structurally intact.
When central stenosis is accompanied by mild mechanical instability (such as a stable Grade I degenerative spondylolisthesis) or facet arthropathy, a decompression alone may risk progressive postoperative slip. However, fusing the segment eliminates motion and exposes adjacent levels to increased mechanical stress.
In appropriately selected patients, Dr. Trapana utilizes an interlaminar motion-preserving stabilization device (such as the coflex® implant):
┌──► 1. Maintains Foraminal Height & Decompression
│ (Acts as a dynamic shock-absorbing bumper between spinous processes)
│
[MOTION-PRESERVING STABILIZATION] ┼──► 2. Preserves Natural Physiological Motion
│ (Allows flexion, extension, and rotation without fusion rigidity)
│
└──► 3. Reduces Adjacent Segment Strain
(Normalizes load transfer without creating rigid stress risers)
| Clinical Metric | Wide Open Laminectomy | Laminectomy + Pedicle Screw Fusion | MISS “Over-the-Top” + Interlaminar Device |
| Tissue Disruption | High; bilateral muscle stripping | Extensive muscle detachment & dissection | Minimal; unilateral muscle-splitting portal |
| Segmental Motion | Retained (but risks instability) | Completely eliminated (0° motion) | Preserved physiological motion |
| Adjacent Segment Stress | Low to moderate | High (Accelerated adjacent wear) | Low (Normal biomechanical load sharing) |
| Blood Loss (EBL) | 150 to 300 mL | 250 to 600+ mL | < 30 to 50 mL |
| Hospital Stay | 2 to 3 days | 3 to 5 days | Outpatient or overnight (24 hours) |
| Rehabilitation Profile | 6 to 8 weeks | 3 to 6 months (waiting for bone union) | Rapid; walking within 2 to 4 hours |
Lumbar spinal stenosis and neurogenic claudication do not require resigning oneself to a sedentary lifestyle, chronic narcotics, or extensive, mobility-destroying spinal fusions. Through minimally invasive “over-the-top” bilateral decompression and motion-preserving interlaminar stabilization, Dr. Evan Trapana provides patients with targeted relief of leg heaviness and pain, restoring posture, mobility, and independence.